how-to
What Tests Can a Gynaecologist Do?
Last Updated: November 5, 2026
Quick Summary
A gynaecologist can do gynaecological tests including a pelvic examination, blood tests, swabs for infection, pelvic ultrasound, hysteroscopy and endometrial biopsy. These tests find the cause of symptoms such as abnormal bleeding or pelvic pain, and screen for problems before symptoms appear. The right test depends on your symptoms, age and history rather than a fixed checklist.
- A pelvic examination is usually the first step and checks the womb, ovaries and cervix.
- Hormone tests need timing around your cycle, such as days two to five for FSH and LH.
- A pelvic ultrasound is painless, uses no radiation and usually takes 10 to 20 minutes.
- Bleeding after menopause should always be checked, even if it is light.
- NHS cervical screening is offered to women and people with a cervix aged 25 to 64.
Table of Contents
- What Gynaecological Tests Are Used For
- Pelvic Examination and Clinical Assessment
- Blood Tests and Laboratory Investigations
- Pelvic Ultrasound: What It Shows and When It Is Used
- Tests for Abnormal Vaginal Bleeding
- Hysteroscopy: Looking Inside the Womb
- Endometrial Biopsy and Tissue Sampling
- Cervical Screening, Colposcopy and Infection Testing
- How Results Are Interpreted and What Happens Next
- Frequently Asked Questions
What Gynaecological Tests Are Used For
Gynaecological tests help find the cause of symptoms such as abnormal bleeding, pelvic pain or unusual discharge. They also screen for problems before symptoms appear. Diagnostic tests for gynaecological health concerns are used to confirm a diagnosis, rule out serious conditions and guide treatment.
Tests fall into a few broad groups:
- Physical assessment to check the pelvis and reproductive organs
- Laboratory tests on blood, urine or swabs
- Imaging such as pelvic ultrasound
- Tissue sampling including biopsy
Each test answers a different question. Some detect infection. Others look for structural problems like fibroids or ovarian cysts. Others check for cell changes that could lead to cancer.
The right test depends on your symptoms, your age and your history. A gynaecologist chooses based on what needs investigating, not a fixed checklist.
For a wider view of how testing supports early detection, see our guide to gynaecological cancer screening.
Pelvic Examination and Clinical Assessment
A pelvic examination is usually the first step. The gynaecologist feels the womb, ovaries and surrounding tissue for size, shape and tenderness. A speculum lets them look at the cervix and vagina directly. A breast examination may also form part of the assessment.
This physical check gives clues that shape the next tests. It is quick and often painless, though you can ask for a chaperone or a pause at any point.
Consent matters here. You should know what is being done and why before it happens. If you feel rushed or unheard, say so.
A common mistake is delaying this first appointment because of nerves. Early assessment often means simpler tests and faster answers.
If this is your first private appointment, our guide on how to prepare for a private gynaecology consultation walks through what to bring and what to expect.
Blood Tests and Laboratory Investigations
Blood tests are among the most useful gynaecological tests. They are quick, low-risk and often reveal the cause of symptoms without further procedures. Most are taken from a vein in the arm and analysed in a laboratory.
Common blood tests include:
- Full blood count to check for anaemia, which heavy periods can cause, and to look for signs of infection or inflammation
- Hormone levels to assess the menstrual cycle, fertility and menopause
- Pregnancy test (usually a urine or blood hCG test) to rule out pregnancy before other tests such as imaging or biopsy
- Tumour markers such as CA125 when ovarian cancer is suspected, though these are interpreted alongside scans and symptoms rather than used alone
- Thyroid function and prolactin when periods are irregular or absent, since both can disrupt the cycle
- Vitamin D and ferritin where fatigue, heavy bleeding or dietary risk factors are present
Hormone tests need timing around your cycle to be meaningful. Follicle-stimulating hormone (FSH) and luteinising hormone (LH) are usually measured in the early follicular phase, around days two to five of a natural cycle. Progesterone is typically checked around day 21 in a 28-day cycle to confirm ovulation. Oestradiol and testosterone may be added when polycystic ovary syndrome or menopause is being investigated. Tell the clinic the date of your last period so the request is timed correctly; a mistimed sample can produce misleading results and lead to a repeat test.
Laboratory tests on swabs can detect gynaecological infections such as bacterial vaginosis, thrush, chlamydia and gonorrhoea. Urine tests can pick up urinary infections that mimic pelvic pain. Some tests, such as chlamydia and gonorrhoea nucleic acid amplification tests, can be done on a self-taken vaginal swab or a first-catch urine sample, which many patients find easier than a speculum examination.
Results are read together, not in isolation. A raised CA125, for example, can occur with endometriosis, fibroids or pelvic infection as well as ovarian cancer, so it is rarely diagnostic on its own. A low ferritin with heavy bleeding points towards iron deficiency anaemia and may prompt treatment alongside investigation of the cause. If a result is borderline or inconclusive, the gynaecologist may repeat it at a different point in the cycle, add a further test, or arrange imaging to clarify the picture.
Watch out: do not start hormone treatment, including combined oral contraception or hormone replacement therapy, without telling the clinic, because it can alter the interpretation of hormone and bleeding-related results.
Pelvic Ultrasound: What It Shows and When It Is Used
A pelvic ultrasound uses sound waves to create pictures of the womb, ovaries and surrounding structures. It is painless and does not use radiation.
There are two main types:
- Transabdominal ultrasound with the probe on your lower belly
- Transvaginal ultrasound with a slim probe inside the vagina, which gives clearer images
Ultrasound can show fibroids, ovarian cysts, endometriosis and a thickened uterine lining.
You lie on a couch, usually for 10 to 20 minutes. A full bladder may be needed for the abdominal scan.

For a detailed walkthrough of the appointment itself, read our article on what to expect from a private gynaecology ultrasound.
Tests for Abnormal Vaginal Bleeding
Abnormal bleeding has many possible causes. Tests for abnormal vaginal bleeding aim to find which one applies to you.
The gynaecologist may start with:
- A pelvic examination
- Blood tests for anaemia and hormone levels
- A pelvic ultrasound
If the lining of the womb looks thick, or bleeding persists after menopause, tissue sampling is often the next step. This may mean an endometrial biopsy or a hysteroscopy.
Age and history guide the choice. Bleeding between periods in a younger woman points to different causes than bleeding after menopause.
Watch out: bleeding after menopause should always be checked, even if it is light. Do not wait to see if it settles.
Hysteroscopy: Looking Inside the Womb
A hysteroscopy lets the gynaecologist look directly inside the womb using a thin camera passed through the cervix. It is one of the most direct gynaecological tests for bleeding and lining problems.
It can find:
- Polyps
- Fibroids inside the cavity
- Scar tissue
- Areas of abnormal lining
The procedure can be done in clinic or under a light anaesthetic. Many women return to normal activity the same day. You may have light bleeding or cramping for a day or two.
Hysteroscopy is often combined with a biopsy so tissue can be checked in the laboratory.
Endometrial Biopsy and Tissue Sampling
An endometrial biopsy takes a small sample of the uterine lining for laboratory testing. It is used to check for cell changes, including early cancer, and to investigate abnormal bleeding.
Other tissue samples include cervical biopsy and, in some cases, dilatation and curettage. Each sends a tissue sample to the lab for a clear diagnosis.
A biopsy can feel like strong period cramps and takes only a few minutes. Results usually return within one to two weeks.
Combining a scan and biopsy in one visit shortens the wait for answers. Our article on combined scan and biopsy clinics explains how this efficient diagnostic process works.
Cervical Screening, Colposcopy and Infection Testing
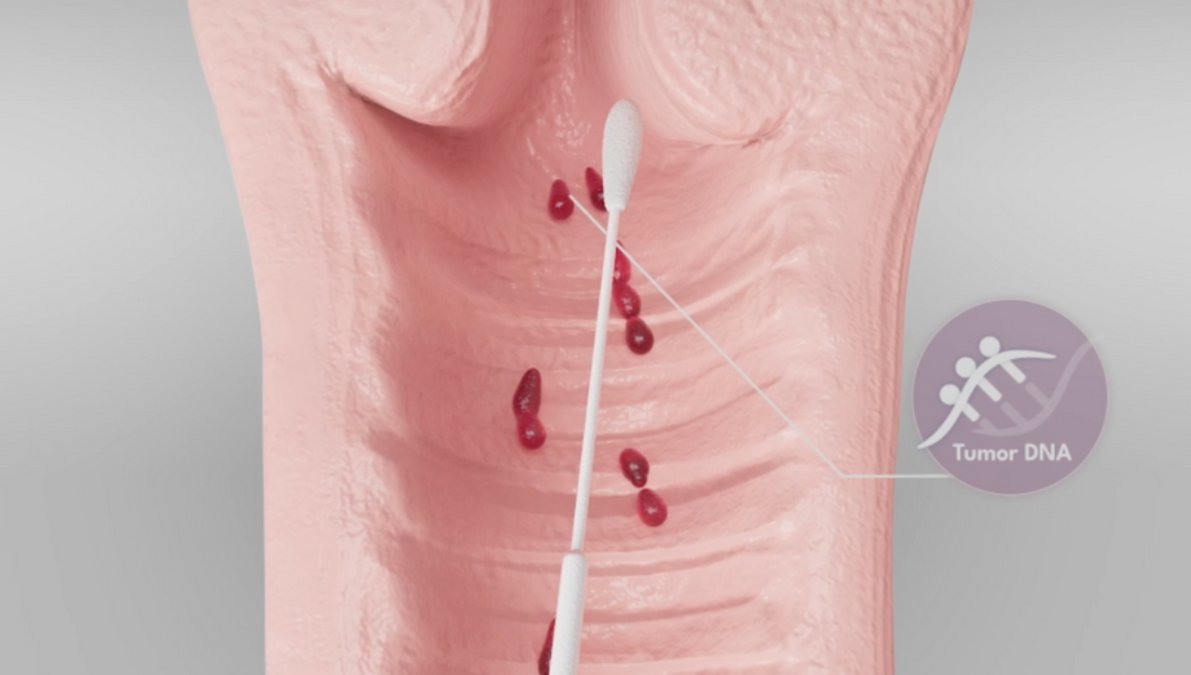
Cervical screening checks for HPV and cell changes that could lead to cervical cancer. In the UK it is offered on the NHS to women and people with a cervix aged 25 to 64, usually every three years up to age 49 and every five years from 50 to 64. Since the move to HPV primary screening, the sample is first tested for high-risk HPV; if HPV is found, the same sample is examined for cell changes, and abnormal results lead to further checks. Routine cervical screening is a prevention programme, not a diagnostic test for symptoms, if you have abnormal bleeding, pain or discharge, you need a diagnostic assessment rather than waiting for your next screening invitation.
Colposcopy is a closer look at the cervix with a magnifier (a colposcope). It is usually offered when screening finds high-risk HPV with cell changes, or when symptoms such as postcoital bleeding need direct assessment. The appointment takes around 15 to 20 minutes. The clinician applies dilute acetic acid to highlight abnormal areas, may take a small cervical biopsy, and in some cases treats abnormal cells at the same visit. You can have a chaperone, and you can ask to pause at any point.
Infection testing uses swabs or urine to detect HPV and common gynaecological infections. Treating infection early prevents complications such as pelvic inflammatory disease and eases symptoms.
Watch out: bleeding after sex, between periods or after menopause should not be attributed to screening alone, ask for a diagnostic assessment even if your last cervical screening was normal.
For more on HPV and when to seek help, read our guide to HPV symptoms and testing.
Cervical screening in the UK follows a set age and interval schedule.
| Item | Value | Note |
|---|---|---|
| Age offered | 25 to 64 | Women and people with a cervix |
| Interval up to age 49 | Every three years | NHS cervical screening |
| Interval from 50 to 64 | Every five years | NHS cervical screening |
| First test on sample | High-risk HPV | HPV primary screening |
| If HPV found | Same sample examined for cell changes | Abnormal results lead to further checks |
| Colposcopy appointment | Around 15 to 20 minutes | Closer look with a colposcope |
How Results Are Interpreted and What Happens Next
Results are read together, not in isolation. A scan, a blood test and a biopsy often combine to give one clear picture.
Most results are normal or show a treatable cause. If something needs follow-up, the gynaecologist explains the options and the timeline. Some findings need monitoring. Others need treatment or a repeat test. Where a scan confirms fibroids, for example, management may range from monitoring to procedures such as a Laparoscopic Myomectomy, and suspected endometriosis can be discussed with an Endometriosis Specialist.
Ask for your results in plain English and for a written plan.
Frequently Asked Questions
What tests can a gynaecologist do?
A gynaecologist can carry out a pelvic examination, blood tests including hormone levels and a full blood count, pregnancy testing, swabs for gynaecological infections, cervical screening and HPV testing, colposcopy, pelvic ultrasound, hysteroscopy, and biopsies such as an endometrial biopsy. Which gynaecological tests you need depends on your symptoms, your age, and your risk factors.
Which tests can investigate abnormal vaginal bleeding?
Tests for abnormal vaginal bleeding usually start with a pelvic examination and blood tests to check hormone levels and blood count. A transvaginal pelvic ultrasound looks at the uterine lining, fibroids and ovarian cysts. An endometrial biopsy samples the lining to rule out cell changes, and a hysteroscopy lets the gynaecologist see inside the womb directly and take targeted tissue if needed. Postmenopausal bleeding is always investigated, even when it happens only once.
Can an ultrasound detect gynaecological cancer?
A pelvic ultrasound can show thickening of the uterine lining, ovarian cysts or masses, and fibroids, which may prompt further investigation. It cannot confirm cancer on its own. Diagnosis comes from a tissue sample, taken by endometrial biopsy, hysteroscopy or colposcopy, examined in a laboratory. Ultrasound is best understood as a triage tool: it tells your gynaecologist whether the next step should be a biopsy or simply monitoring.
How long do gynaecological test results take?
Ask your gynaecologist for the expected turnaround time of each test. Ultrasound and hysteroscopy findings are discussed at the appointment itself. Ask your gynaecologist when to expect each result and who will contact you, so you are not left chasing answers between appointments.
If you are facing unexplained symptoms or waiting too long for answers, Mr Javaid Muglu offers expert gynaecological care with rapid assessment and a clear plan. Our One Stop clinics combine consultation and scan in a single appointment, and we specialise in advanced laparoscopic surgery and gynaecological oncology. Get started with Mr Javaid Muglu and take the first step towards peace of mind.